


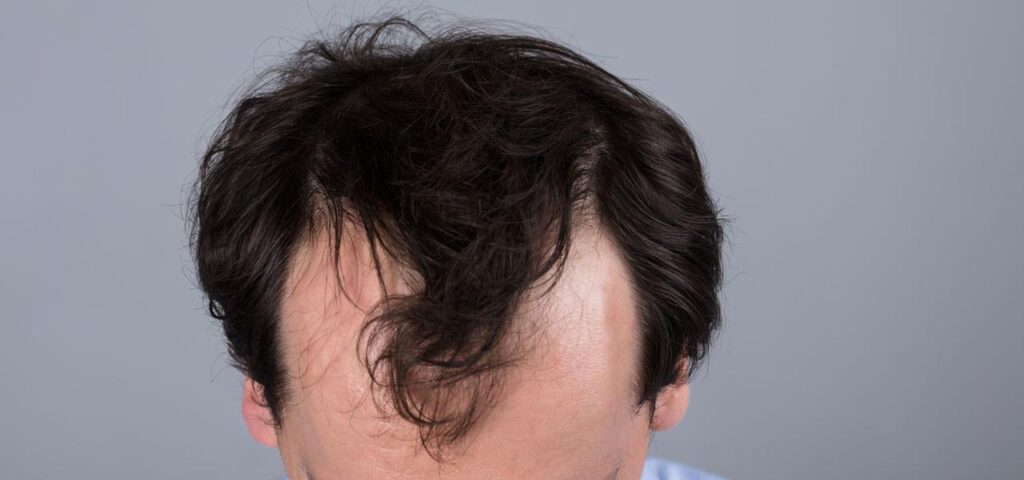
Androgenetic alopecia is the most common cause of hair loss, affecting as many as 70–80% of men and 30–40% of women. This genetically determined condition stems from the hypersensitivity of hair follicles to dihydrotestosterone (DHT). If you notice a receding hairline or thinning hair, learn about the causes, symptoms, and effective treatment methods.
What is androgenetic alopecia?
Androgenetic alopecia is a chronic condition with a genetic and hormonal basis. It is characterized by the hypersensitivity of hair follicles to androgens—male sex hormones present in both men and, at lower concentrations, women. 5α-dihydrotestosterone (DHT) plays a key role in this process; it is a derivative of testosterone formed through enzymatic conversion mediated by 5α-reductase.

You can use the infographic on your website by copying the code below:
Symptoms and stages of androgenetic alopecia
The course of the disease varies by gender; therefore, standardized scales for assessing disease severity are used in clinical diagnosis.
In men: Norwood-Hamilton scale
Hair loss is classified according to the Hamilton-Norwood scale. Hair loss typically affects the fronto-temporal regions first, followed by the parietal area. Thinning spreads towards the temples and the crown, eventually leaving a fringe of hair at the back of the head (occipital region) and around the temples.
Diagnosis relies primarily on the patient interview. The doctor will ask about the onset of symptoms, the progression of hair loss, and any co-existing medical conditions. Next, the doctor carefully examines the scalp and performs a hair pull test by tugging on clusters of hair in several locations; a positive result is indicated if approximately 10 hairs are pulled out. Diagnosis also involves trichoscopy using a dermatoscope, allowing the specialist to assess the condition of the hair shafts, follicles, and scalp.
The treatment of androgenetic alopecia involves the use of drugs that block the 5α-reductase enzyme—such as finasteride, which also inhibits the production of DHT, a derivative of testosterone. The drug blocks hair loss and stimulates hair growth.
Another pharmacological agent that reduces DHT levels is dutasteride. However, an increasing number of specialists are employing a modern technique that utilizes platelet-rich plasma. The preparation is derived from the patient’s own blood and administered to the scalp via mesotherapy.
Norwood-Hamilton scale

In women: Ludwig scale
Women also struggle with troublesome androgenetic alopecia, which typically occurs during the perimenopausal period. According to numerous studies, it is estimated that androgenetic hair loss affects approximately 50% of women over the age of 50–55.
It is hard to overlook the problem of hair loss in women, as it presents with characteristic symptoms. A particular cause for concern is an increase in the daily number of hairs lost—specifically, more than 100. If a woman notices more strands than usual on her hairbrush or hands, and the volume of her hair has significantly decreased, it is advisable to consult a trichologist or dermatologist. These specialists can diagnose the issue and initiate appropriate treatment. Since the symptoms primarily involve hair loss in the central part of the scalp, the condition can be quickly identified.
Ludwig scale
What are the causes and treatment methods for androgenic alopecia in women?
The primary cause of androgenetic alopecia in women is hormonal imbalance resulting in elevated levels of male sex hormones—specifically testosterone. This condition typically stems from various medical disorders, such as hyperthyroidism, hypothyroidism, PCOS, or Hashimoto’s disease. Other contributing factors include:
- a restrictive diet low in vitamins and minerals,
- impaired scalp circulation,
- diabetes.
Fortunately, androgenetic alopecia in women can be effectively treated. Thanks to detailed diagnostics—which include blood tests and an assessment of the clinical picture—a doctor can decide to:
- the introduction of medications containing minoxidil, which is applied to the scalp (in liquid form),
- the introduction of oral medications that block receptors and inhibit the negative effects of elevated testosterone,
- performing a hair transplant.
Scalp mesotherapy also works exceptionally well, supporting treatment and stimulating hair growth.
Androgenetic alopecia is a common form of hair loss caused primarily by hereditary and hormonal factors. Symptoms differ between men and women, but both groups can experience significant hair thinning.
– Piotr Turkowski, MD, PhD
Ocena ryzyka łysienia androgenowego
Sprawdź swoje predyspozycje do łysienia androgenowego w mniej niż minutę
Diagnostics: What is worth testing?
A blood test will help doctors understand the causes of hair loss by identifying potential hormonal imbalances. Here are some of the most commonly recommended blood tests:
| Test | What it measures | Why it is important |
|---|---|---|
| Total testosterone | Blood testosterone level | The primary substrate for DHT production, which initiates follicle miniaturization. |
| DHT (Dihydrotestosterone) | Concentration of the active metabolite | The primary hormone responsible for hair follicle miniaturization. |
| SHBG | Sex hormone-binding globulin | Determines the pool of free, biologically active testosterone in the body. |
| TSH, FT3, FT4 | Thyroid function | Thyroid disorders exacerbate or mask the problem of hair loss. |
| Ferritin / Iron | Body iron stores | Iron deficiency is a common cause of concurrent telogen effluvium. |
Modern treatment methods at PT CLINIC
Combating androgenetic alopecia requires a comprehensive approach. Modern aesthetic medicine and trichology offer proven therapeutic protocols:
- Targeted pharmacotherapy: Use of substances that inhibit the enzyme 5α-reductase (e.g., finasteride) and topical preparations that stimulate microcirculation and nourish hair follicles (e.g., minoxidil).
- Biostimulating therapies (e.g., platelet-rich plasma): The use of growth factors contained in the patient’s concentrated plasma to stimulate dormant follicles to regenerate.
- Scalp needle mesotherapy: Direct delivery of vitamin cocktails, amino acids, and peptides deep into the skin.
- Hair transplant (FUE method): An advanced surgical procedure involving the precise extraction of individual follicular units from a donor area (typically the back and sides of the head) and transplanting them into areas affected by thinning or complete hair loss. It is a permanent and highly effective solution that allows for the restoration of a natural hairline and increased hair density in areas where follicles have been permanently lost.
New therapeutic approach in 2026: Combination therapies
Modern guidelines for treating androgenetic alopecia are shifting away from single-modality approaches in favor of combination therapies. The key to permanently halting follicle miniaturization lies in simultaneously targeting the root cause from within—using pharmacotherapy to block DHT—while stimulating microcirculation and tissue regeneration from the outside through advanced in-office procedures such as platelet-rich plasma (PRP), exosomes, or targeted mesotherapy. Such an integrated treatment plan, tailored to the individual following a trichoscopic examination, yields significantly better and more stable results than monotherapy.
Treatment efficacy in light of clinical trials
Years of scientific observations and clinical studies confirm the high efficacy of modern therapeutic methods:
- Oral pharmacotherapy (e.g., finasteride): Inhibits the further progression of hair loss in approximately 86–90% of patients and results in measurable new hair regrowth in over 65% of patients after 1–2 years of regular use.
- Topical treatment (e.g., minoxidil): Prolongs the active hair growth phase (anagen) and stimulates follicle vascularization, resulting in increased hair density.
- Biostimulating therapies (PRP/plasma): Clinically proven to significantly increase density and improve hair shaft thickness, particularly in protocols combined with pharmacotherapy or following an FUE transplant.
Source of clinical data: Official FDA multicenter registry studies and scientific publications in the fields of dermatology and the treatment of androgenetic alopecia (including PubMed / DermNet archives).
The role of diet and lifestyle in supporting therapy
Diet cannot replace treatment that addresses the root cause, yet it plays a crucial role in the health of hair follicles. It is advisable to adopt a low-glycemic index (GI) approach, as fluctuations in glucose levels and insulin resistance exacerbate androgen-related processes.
- Omega-3 fatty acids (ALA and GLA): They naturally inhibit 5α-reductase activity (sources: vegetable oils, nuts, pumpkin seeds).
- Complete protein and sulfur-containing amino acids: Building blocks of the hair shaft (meat, fish, legumes, eggs).
- B vitamins, vitamin D, zinc, and iron: Key micronutrients for proper cell division in the hair matrix.

Hello. I was diagnosed with PCOS recently. Which makes sense why all this years the hair on my crowns had been thinning. My gynae prescribed YFS supplements and Glucophage. Hopefully it can help with my hair as well.
Thank you for sharing your experience. PCOS is indeed a common cause of hair thinning in women due to hormonal imbalance. The treatment prescribed by your gynecologist can help regulate those hormones, which may gradually improve hair density. Combining it with proper scalp care and medical hair treatments often gives the best results.